


Non-Surgical Slipped Disc Treatment in KL: Surgery or Not?
Non-surgical slipped disc treatment comes first in my approach, and surgery comes last. Treating a slipped disc without surgery is where I start with patients in Kuala Lumpur, once the examination shows it is safe to try. A few cases need surgery sooner: a disc whose broken piece has come away completely, an infection, and the urgent nerve signs set out below.
Trials comparing early surgery with prolonged conservative care found the long-term results alike. A Dutch trial followed 283 people whose sciatica came from a slipped disc. Early surgery eased their leg pain sooner. At one year, and again at five, pain and disability were much the same in both groups. In my personal opinion, injections are better avoided, and so is nucleoplasty, a needle procedure that uses radiofrequency energy on the disc's soft center.
Non-surgical care, as I mean it, is focused: planned from the examination and the MRI, free of twisting, and reviewed at set visits. The sections below cover the trials, the cases that need an operation, the treatment itself, injections, repeat surgery and success rates.
For more information about non-surgical slipped disc treatment, contact the Bukit Damansara (KL) main center: WhatsApp+60 17 269 1873 Call+603 2093 1000
Non-Surgical Slipped Disc Treatment: Key Takeaways
| Question | Short answer |
|---|---|
| How do I know if my slipped disc needs surgery? | The examination and the MRI decide, not the pain score. In my approach, surgery is weighed for a sequestered disc, an infection, the urgent signs in the last row, or focused care, properly given, that has not worked. |
| How often does a slipped disc end in surgery? | In the Dutch Sciatica Trial, 46 percent of the people given prolonged conservative care had surgery within five years. Their care was set by family doctors and aimed mainly at resuming daily activities, not the focused care described here. |
| Does surgery put an end to a slipped disc problem? | In my experience it does not, and operations often have to be repeated. In Finland, 25,359 people had surgery for a lumbar disc herniation, and their risk of another lumbar operation reached 18.9 percent over nine years. |
| Are injections a step before surgery? | Not in my plans. A 2012 review of 23 placebo-controlled trials in sciatica found that epidural steroid injections had only a small effect on leg pain, and only in the short term. |
| What does non-surgical treatment leave out? | Cracking or twisting a damaged disc, hard neck pulls, heavy massage, someone walking on the back, hot packs, early stretching, swimming laps and yoga. Each can strain or inflame the disc it was meant to help. |
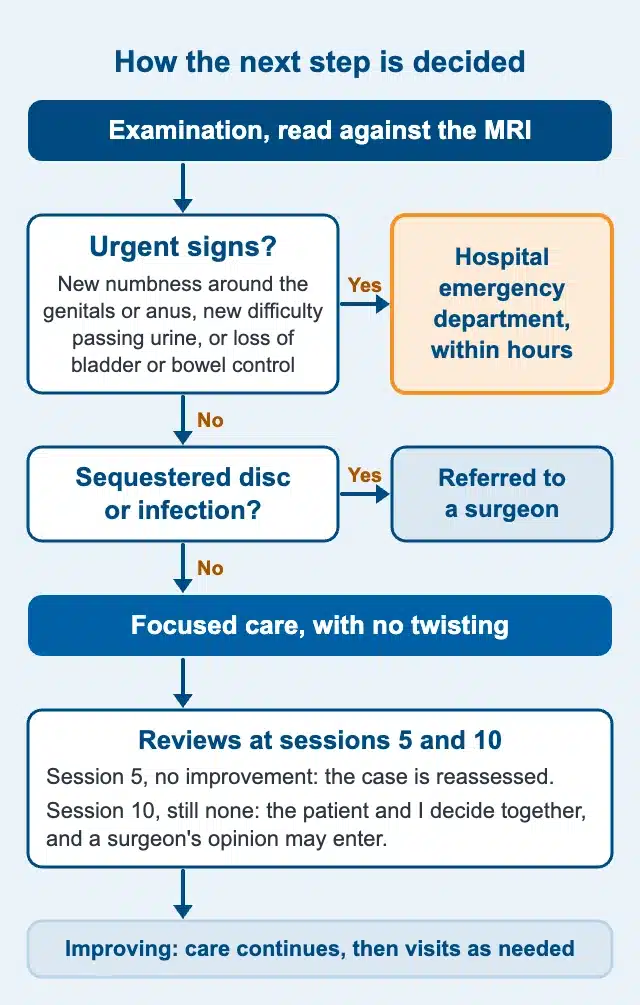
| How is progress judged before surgery is weighed? | The first visit's tests are repeated at two review points, which I explain in Is Chiropractic Safe? 13 Questions Answered. If the fifth session brings no improvement, the case is reassessed. If the tenth still shows none, the patient and I decide together whether to go on. |
| Which signs need a hospital straight away? | New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention. Go to a hospital emergency department straight away, within hours. |
Page Guide: The Decision, Section by Section
- Slipped Disc Surgery vs Conservative Care: What Trials Found
- Arranging an Assessment Before Any Operation
- When Does a Slipped Disc Need Surgery?
- What Non-Surgical Slipped Disc Treatment Involves
- Condition-Based Conservative Care That Does No Harm
- Injections and Nucleoplasty: My Personal Opinion
- Keyhole and Open Slipped Disc Surgery: What Remains Afterward
- How I Read a Surgery Success Rate
- Daily Habits Alongside Treatment
- Video: My Talk on Disc Stages, Sciatica and Surgery
- Where a Slipped Disc Causes Symptoms
- Fees for Treatment at CSC
- Slipped Disc Surgery or Not: Questions Answered (FAQ)
Slipped Disc Surgery vs Conservative Care: What Trials Found
Three sources compare surgery for a lumbar slipped disc with care that avoids it, and over time all three found the results alike. None of them tested the focused care described on this page, so each is given here for what it measured.
A 2010 review gathered 18 trials covering 1,671 people with a lumbar disc herniation and leg symptoms. In two high-quality trials, advice alone did less well than microdiscectomy in the short term and as well in the long term. Microdiscectomy is the usual operation that removes the part of the disc pressing on a nerve. The review also found moderate evidence that stabilization exercises did better than no treatment (Hahne and colleagues, 2010).
The Dutch Sciatica Trial then took 283 adults with six to twelve weeks of severe sciatica and a herniation confirmed by MRI. Half were assigned to early surgery, and 89 percent of them had it, after an average of 2.2 weeks. The other half had prolonged conservative care, with surgery if it was needed. In that group, 39 percent had surgery within the first year, after an average of 18.7 weeks.
Leg pain eased faster after early surgery, and those patients felt recovered sooner. Yet disability over the first year did not differ significantly between the groups. The authors judged the one-year outcomes similar (Peul and colleagues, 2007).
Five years on, 231 of the 283 were followed up again. Pain and disability still showed no significant difference between the groups. By then, 46 percent of the conservative group had had surgery because of severe leg pain and disability (Lequin and colleagues, 2013).
What that conservative care was matters. It was set by family doctors and aimed mainly at resuming daily activities. The authors concluded that prolonged conservative care might give a fair chance for pain and disability to resolve without surgery. The risk is a later operation, after a longer spell of sciatica.
None of these trials tested focused care. That means an examination read against the MRI, non-rotatory methods, treatment of the tissues around the disc, and reviews at set visits. In my view, that is the comparison patients actually face. So I judge each case by its own examination and progress, not by a trial average.
Arranging an Assessment Before Any Operation
If an operation has been suggested for a slipped disc, a non-surgical assessment can come first, unless the urgent signs below are present. To arrange one, call or WhatsApp either Kuala Lumpur center. The first visit examines the spine and the nerves of the legs or arms, and reads the findings against any MRI already taken. Bring the MRI images themselves, on CD or film, with the reports and any letter from a surgeon.
- Bukit Damansara (KL, main center): Call +603 2093 1000 or WhatsApp +60 17 269 1873 to see the Bukit Damansara / KL center.
- Bandar Sri Damansara (KL): Call +603 6262 5777 or WhatsApp +60 12 455 6939 to see the Bandar Sri Damansara center.
For travel, parking and opening hours, see Bukit Damansara address, hours and phone or Bandar Sri Damansara address, hours and phone. Both centers are listed on the page of CSC's Kuala Lumpur locations.
When Does a Slipped Disc Need Surgery?
In my approach, an operation is weighed in two situations. The first is a severe case: a sequestered disc, an infection, or the urgent signs described below. The second is focused conservative care, properly given, that has not worked.
The word fragmented on an MRI report needs care. Partial fragmentation can still respond to focused conservative care, on two conditions. A thorough assessment must first find none of the urgent signs. The care must then be delivered by an experienced clinician in a highly focused, efficient and precise way. When the piece tears away completely, the disc is fully fragmented, also called sequestered, and that is a severe case.
Invasive procedures have their place, and some cases need them. In Sciatica vs Slipped Disc I say it directly: "There are times I cannot help." When the examination shows such a case, I tell the patient at once and refer them to a surgeon.
If you are deciding between surgery and non-surgical treatment for a slipped disc with back or leg pain, new or worsening numbness around your genitals, between your genitals and anus, or around your anus needs urgent medical attention: a thorough assessment at a hospital emergency department straight away, within hours. New difficulty passing urine needs the same, even if bladder and bowel control remain intact, and so does any loss of that control. These symptoms can have several causes. Some may call for an invasive procedure, but the symptoms alone do not establish that surgery is necessary; assessment helps identify the cause and guide care decisions.
Leg weakness that keeps getting worse should not be ignored. It calls for a careful assessment by a competent provider, and conservative care can continue only while the weakness itself is improving.
8 Checks That Decide the Next Step
These are the eight checks I make before surgery comes into the discussion:
- Are the symptoms mild to moderate? Then the examination and focused non-surgical care come first. Surgery is not a first step for mild or moderate symptoms.
- Do the symptoms travel into an arm or a leg? That can mean a nerve is involved. A structured examination finds the source and the next step.
- Do the symptoms persist or keep coming back? Then a full assessment is worth having, to find the source rather than chase each flare.
- Is daily activity becoming limited? Difficulty sitting, standing or moving is a reason to have the spine assessed.
- Does every slipped disc need surgery? No. In my approach, surgery is held back until focused conservative care, properly given, has not worked, unless the case is severe.
- Has focused care been tried? Surgery may be discussed when structured non-invasive care has not led to meaningful improvement.
- What do the findings show? Decisions rest on the examination, imaging when it is needed, and how far the symptoms limit daily activity.
- Has the source been found early? Knowing where the symptoms come from shows whether non-surgical care or a further medical opinion is the right next step.
Where a disc stands in the stages of damage shapes these answers too. The slip disc guide to causes and stages follows a disc from the first damage to a free fragment. The guide to stage-by-stage slip disc treatment in Kuala Lumpur matches the methods to each stage.
What Non-Surgical Slipped Disc Treatment Involves
Non-surgical slipped disc treatment helps a damaged disc settle with movement, exercise and hands-on care, without surgery or injections. It aims to improve how the spine moves, ease the pressure on the disc, and help the muscles around the spine support it better.
At CSC, chiropractors and physiotherapists work on the same case, bringing chiropractic, physiotherapy, spinal decompression and guided rehabilitation together. Programs that combine physiotherapy rehabilitation, chiropractic spinal mobilization, decompression and targeted exercises are usually explored before anything more invasive is considered.
Non-surgical, as I use the word, means focused conservative care. Each plan starts from the examination and the MRI, and every method in it has a reason in those findings. The joints, muscles, fascia and nerves around the disc are treated as well. In Sciatica vs Slipped Disc I explain why. An irritated nerve also damages the muscles and their covering, the fascia, so treating one part alone leaves the rest in place.
The Examination That Decides Each Plan
Treatment without surgery depends on the examination more than on any single method. In my view, finding the diagnosis and its cause is the most important part of care. A cause left in place brings the symptoms back.
The assessment starts with the health history and the symptoms. Posture and movement come next, then orthopedic and neurological tests and muscle testing. Together they show whether the symptoms come from a disc, a joint, the muscles or an irritated nerve. A suspected disc problem gets an MRI, since I never guess at a final diagnosis. An MRI or X-rays taken earlier are read against the examination.
The findings and the proposed plan are explained before any care starts. A plan is offered only when the case suits conservative care.
Methods Used Without Surgery at CSC
Each method below is used only when the examination calls for it:
- Chiropractic manipulation that is non-rotatory using the Activator instrument, with no cracking or twisting of a damaged disc
- Flexion-distraction: the table bends the lower back gently, a little at a time, to open the affected segment
- Spinal decompression therapy: a gradual, controlled pull aimed at one level of the spine
- High-intensity laser therapy, which warms the deep tissue only mildly
- Therapeutic ultrasound, for the soft tissue next to the joints and the disc
- Shockwave therapy, for muscles beside the spine that have stayed tight for a long time
- Trigger point and myofascial work on the muscles and fascia that an irritated nerve has tightened
- Cold therapy by machine, with the heat setting left off whenever a disc or facet joint is involved
- Kegel exercises, buttock contractions and side-lying leg raises, from the first day
- Guided rehabilitation from about the fifth to seventh session, once the spine is stable
- Calf stretches and other stretching only after the acute phase has passed
Spinal decompression systems such as RxDecom® are designed to help reduce mechanical stress placed on spinal discs while supporting spinal mobility during rehabilitation programs.
A small trial took 30 people with a disc herniation and chronic low back pain. Decompression or ordinary traction was given with physiotherapy, three times a week for four weeks. Both groups improved in pain, disability and straight leg raising, with no significant difference between them (Choi and colleagues, 2015).
NSD Therapy® at CSC
NSD Therapy® is the integrative approach CSC uses for non-surgical slipped disc treatment in Kuala Lumpur. It is a combination rather than one treatment: chiropractors and physiotherapists working with spine technology. Spinal decompression, physiotherapy-based rehabilitation, gentle chiropractic methods and guided strengthening are chosen from the examination, to support the spine's stability and movement.
Care is kept within what the patient can comfortably tolerate, and the patient tells the clinician at once if anything hurts. Discomfort during care means it is being done too aggressively. My motto has always been "No pain, more gain."
Progress is measured against the first visit's tests, the patient's pain ratings and what has changed in daily life. I use two review points; my video Is Chiropractic Safe? 13 Questions Answered explains them. A case with no improvement by the fifth session is reassessed. If none has come by the tenth session, the patient and I decide together whether to go on. A surgeon's opinion may then enter the discussion.
Condition-Based Conservative Care That Does No Harm
Choosing to avoid surgery is only half of the decision. In Sciatica vs Slipped Disc I give the other half: the care must be "condition based and appropriate." Then I narrow it further: "Ones that don't harm."
While a disc is damaged, these stay out of my plans:
- Cracking or twisting the spine. In the same video I warn that a damaged disc should not be cracked or twisted, even by a very experienced chiropractor.
- A hard yank on the neck while someone pulls on the ankles. I name it there too, among the things I would not recommend.
- Forceful massage on the damaged level, or anyone walking on the back. I list both in the same video. Each presses hard on the level that is already damaged.
- Hot packs and heating pads. Heat "also increases inflammatory processes," a warning from my Back Pain to Leg Pain talk. Inflammation is among the earliest changes in a damaged disc.
- General stretching while the disc is irritable. My words in the same talk: "If you have a disc problem, you do not do that." Hard pulls on the hamstrings also stretch the sciatic nerve that runs behind them.
- Swimming laps. The kicking and turning bend and twist the spine with every stroke; walking in water is gentler.
- Deadlifts and heavy gym lifting. In the talk I tell patients to leave deadlifts out of any gym routine.
- Yoga, even in classes described as gentle. Its deep bends and twists load the disc.
The guide to choosing a slipped disc chiropractor in KL sets out my checks before any adjustment. It also covers the methods I use instead of twisting.
Injections and Nucleoplasty: My Personal Opinion
Injections are often offered as a middle step between conservative care and surgery. In Sciatica vs Slipped Disc I list what some people offer for a slipped disc. It runs from cracking the back to "a little bit of steroid injections" or "a little surgery." My answer there: "I wouldn't recommend any of those."
In my personal opinion, injections are better avoided for a slipped disc, and so is nucleoplasty. In my view, nucleoplasty has no value. Over the years, hundreds of patients, if not more, have come to me after it with no improvement whatsoever. In many instances they were worse. Where an invasive procedure is truly needed, my advice is to stay away from radiofrequency treatment of the disc or the facet joints. Facet joint injections are on the same list.
The same goes for trigger point and myofascial injections into the muscles around the spine. My Back Pain to Leg Pain talk covers them too: there is no need to go that route, and the injections carry side effects. Those muscles and their fascia do need treatment, and at CSC they are treated with trigger point and myofascial work instead.
Research supports parts of this view. A 2012 review pooled 23 placebo-controlled trials of epidural steroid injections for sciatica. It found a small effect on leg pain and disability in the short term. At a year or more, the effects were smaller and not statistically significant. The authors wrote that the small size of the effect "raises questions about the clinical utility of this procedure" (Pinto and colleagues, 2012).
Heat treatment inside the disc has been tested against a sham as well. A double-blind trial took 20 people with chronic low back pain from a disc. A radiofrequency probe in the disc's outer wall did no better than the sham. Recruitment was stopped early, and the authors would not recommend the treatment (Kvarstein and colleagues, 2009).
Keyhole and Open Slipped Disc Surgery: What Remains Afterward
Keyhole surgery is often described as the small option. In my view, a keyhole is still an incision. The surgeon moves a probe and a camera through the tissue at several angles, and that can disturb or damage what surrounds the disc.
In my experience, no operation returns a disc to the way it was. Surgery often has to be repeated, and in my view it never brings the problem to an end. That is why I keep it as the last option, for the severe cases and for focused care, properly given, that has not worked.
A Finnish study followed 25,359 people operated on for a herniated lumbar disc between 1987 and 1995. Of them, 12.3 percent went on to another lumbar operation, a cumulative risk of 18.9 percent over nine years. The risk was higher for people operated on in the later years of the study (Keskimäki and colleagues, 2000).
Repeat operations appeared in the Dutch trial too. Within five years, 9 of the 125 people who had early surgery (7 percent) needed another disc operation. So did 8 of the 66 operated on later (12 percent) (Lequin and colleagues, 2013).
The guide on spine surgery risks and non-invasive alternatives describes the operations themselves and what to weigh before agreeing to one.
How I Read a Surgery Success Rate
Success rates for spine operations sound reassuring. During my Back Pain to Leg Pain talk I take up the 90 and 95 percent figures quoted for laminectomy, discectomy, foraminotomy and fusion. The first three remove bone or disc pressing on a nerve, and fusion joins two vertebrae. I also mention the 95 percent quoted for nucleoplasty.
Then I look at the word itself: "Success is defined as any measure of improvement." By that definition, a pain rated 10 out of 10 that drops to 9.99 counts as a success. It is a success on paper, "but it wouldn't be successful to you."
So I read every success rate with three questions beside it: what was measured, how much it changed, and for how long. The trials above measured leg pain, disability and the patient's own sense of recovery over one and five years. Those are the figures I give weight to.
Daily Habits Alongside Treatment
Treatment fills only a small part of each day. In Sciatica vs Slipped Disc I put it in numbers: "I see a patient, 30 minutes, two hours." Then I ask: "What about the other 22 hours?"
Asked about the neck during the Back Pain to Leg Pain talk, I answer: "The most important thing is to make lifestyle changes." In the same talk I urge patients to make those changes while they are still hurting. Once the pain goes, the changes tend to be forgotten until it comes back.
With back pain, I ask patients to sit for no more than 15 to 20 minutes at a time. Then they stand or walk for 30 seconds to a minute. Without back pain, sitting for 30 to 40 minutes between breaks is fine. Sleep, lifting, driving, cold packs and the first exercises are set out in the guide to what helps a slipped disc, habit by habit.
Video: Desk Posture Mistakes
In this video, I show common desk posture mistakes. Chair height, monitor position, keyboard placement and sitting habits all change the load on the spine during work or study. Before long desk work, set the chair, monitor and keyboard the way the video shows.
The chapters and an edited transcript of this video are on the Desk Posture Mistakes video page.
Video: My Talk on Disc Stages, Sciatica and Surgery
This is the full recording of my Back Pain to Leg Pain talk. Most of the views on this page come from it, from the stages of disc damage to injections, surgery and success rates.
Tip for viewers: the slipped disc discussion begins around 28:49 in the video. The part on cracking, injections and surgery starts around 1:33:12.
To jump to a part of this talk, see the chapter list on the Back Pain to Leg Pain video page.
Duration: 1 hour 47 minutes | Disc stages, sciatica and where surgery fits
Where a Slipped Disc Causes Symptoms
Slipped disc is the common name for a spinal disc that has been damaged. Its outer fibers have weakened, letting the disc swell or its soft center push outward. Reports call it a disc bulge, a protrusion or a herniated disc, depending on the stage. I use the name loosely myself, and my Back Pain to Leg Pain talk says why: "in reality, discs don't slip."
A slipped disc can affect how the spine moves, the nearby nerves, and everyday activities such as sitting, standing or lifting. Spinal discs work together with the muscles, joints and ligaments, so a change in one structure can affect the whole spine. Which symptoms appear depends on the level involved.
Some people feel only stiffness or localized back pain. Others notice symptoms traveling into an arm or a leg when the nerves become irritated.
In the neck, disc problems may lead to neck pain, reduced neck movement or lasting neck stiffness or pain. Over time, changes in the cervical discs and joints can be part of cervical spondylosis. That can affect posture, movement and how sensitive the nerves are.
In the mid-back, disc changes may add to upper back pain, tension between the shoulder blades or ongoing neck and upper back issues. In the lower spine, disc irritation or degeneration may bring lower back pain, stiffness and limited movement.
When a disc change irritates or presses on a spinal nerve, the result can be sciatica. Its symptoms travel from the lower back into the buttock or leg.
Fees for Treatment at CSC
Each item of care at CSC has its own fee. The cost of a plan depends on the examination findings, which methods are used and how many visits are needed. The chiropractic price in Kuala Lumpur page sets out each chiropractic fee, starting with the examination. The physiotherapy fees in Kuala Lumpur page does the same for physiotherapy. The fee for a plan is explained and agreed before care begins.
Slipped Disc Surgery or Not: Questions Answered (FAQ)
Can a slipped disc get better without surgery?
Yes, a slipped disc can improve without surgery, though in my experience it is never fully reversed. Surgery cannot restore a disc to how it was before the damage either. What lasts depends on what happens after the active care plan ends.
The home exercises and stretches given at the end of that plan, maintenance visits as needed and the daily habits all carry on. People who keep them up give the improvement a better chance of lasting. Those who neglect the problem for years are more likely to have flare-ups.
What are the common signs of a slipped disc?
The most common sign is no sign at all. My Back Pain to Leg Pain talk makes the same point: disc damage most often causes no symptoms. When symptoms do appear, they include stiffness, pain in the neck or back, and pain that travels into an arm or a leg.
In Sciatica vs Slipped Disc I describe the usual sequence in the leg. Pain comes first. Later it "turns into numbness and tingling," and in time the leg can grow weak. A cough or sneeze that sends pain through the back is another common sign.
What does the first examination involve?
A full history, a physical examination and the scans. From arrival to leaving, a first visit lasts anywhere from 30 minutes to two hours. The more complex the problem, the longer it takes. I never rush it, since a problem that looks mild can call for a closer look at other areas.
Before the visit, note when and how the problem began, how it has changed since, and every treatment already tried. Add the questions to ask. Wear comfortable clothing, and consider bringing a family member, since each person remembers different things.
What is non-surgical slipped disc treatment?
It is treatment of a slipped disc without an operation or injections, carried out as a sequence rather than a single method. The irritated segment is calmed first. Movement is then restored without twisting the spine, strength is rebuilt around the disc, and full activity returns, with maintenance after that.
Chiropractors and physiotherapists carry out that sequence together at CSC, choosing each method from the examination. The step-by-step guide to slipped disc treatment in KL sets out each stage.
Is physiotherapy useful for a slipped disc?
Yes, as part of a combined plan. In Is Chiropractic Safe? 13 Questions Answered I explain the depth involved: the spinal disc sits 6 to 10 centimeters below the skin. An adjustment alone does not reach that deep, and that is where physiotherapy comes in. My advice in that video is not to pick one or the other: "Choose both."
At CSC, the physiotherapy side includes the early exercises, trigger point and myofascial work, laser, ultrasound and shockwave. Guided strengthening follows once the spine is stable.
Why do symptoms travel into the leg or arm?
Because a disc sits right beside the nerve roots leaving the spine. Behind the disc, the ligament is thinner than at the front. So a damaged disc pushes backward, toward the nerves, and can press on or inflame a root. The symptoms then follow that nerve.
From the neck they run into the shoulder, arm and hand. For the lower back, Sciatica vs Slipped Disc explains that four nerves, from L4 to S2, join under the buttock to form the sciatic nerve. It runs down the back of the leg.
How long does the treatment take?
No fixed number of sessions applies to everyone. The stage of the disc, the level, how long the symptoms have lasted and daily habits all change it. What I can describe is the pattern. The first exercises start at once, and the wider exercise program usually begins around the fifth to seventh session, once the spine is stable.
The active plan ends at MMI, maximum medical improvement, reached when retesting shows no further change after two to three more weeks of care. Visits are then as needed.
When should I get my slipped disc checked?
Get it checked once symptoms linger, return again and again, spread into an arm or a leg, or start limiting sitting, walking or sleep. Numbness, tingling or weakness call for an examination sooner, before the problem flares again. New numbness around the genitals or anus, new difficulty passing urine, or loss of bladder or bowel control needs urgent medical attention. Go to a hospital emergency department straight away, within hours.
Can posture affect a slipped disc?
Yes, because posture sets the pressure inside the disc. My Back Pain to Leg Pain talk gives rough figures: about 25 mmHg (millimeters of mercury) lying down and 100 standing. Leaning forward pushes it to 150 to 200, and sitting to about 250. A disc draws in fluid and nourishment only while that pressure is low, so long, slumped sitting starves it and sleep feeds it.
Positions held in yoga load the disc the same way, so yoga must be avoided with a slipped disc. In the same talk my advice is to "not do yoga at all," however good it feels.
Where does spinal decompression fit in?
Often, as one part of the plan rather than the whole of it. Decompression at CSC is a gradual pull on a table, adjusted to the level of the spine involved, and it works alongside the other methods. Older patients with a narrowed spinal canal or worn joints have lighter, shorter sessions.
Decompression is also different from a sudden yank on the neck or a home inversion table. The page on spinal decompression therapy in Kuala Lumpur explains the difference.
How to Read This Guide
This guide sets out my approach to a slipped disc when surgery is being considered. I write it in the first person, and each view taken from one of my videos or talks names that video. Studies appear by first author and year; their results describe groups of people, not one person's spine. No page can examine anyone or say whether a particular disc needs an operation. An examination read against the MRI does that.
Peer-Reviewed References
- Hahne AJ, Ford JJ, McMeeken JM. Conservative management of lumbar disc herniation with associated radiculopathy: a systematic review. Spine (Phila Pa 1976). 2010;35(11):E488-E504.
- Peul WC, van Houwelingen HC, van den Hout WB, et al. Surgery versus prolonged conservative treatment for sciatica. N Engl J Med. 2007;356(22):2245-2256.
- Lequin MB, Verbaan D, Jacobs WC, et al. Surgery versus prolonged conservative treatment for sciatica: 5-year results of a randomised controlled trial. BMJ Open. 2013;3(5):e002534.
- Choi J, Lee S, Hwangbo G. Influences of spinal decompression therapy and general traction therapy on the pain, disability, and straight leg raising of patients with intervertebral disc herniation. J Phys Ther Sci. 2015;27(2):481-483.
- Pinto RZ, Maher CG, Ferreira ML, et al. Epidural corticosteroid injections in the management of sciatica: a systematic review and meta-analysis. Ann Intern Med. 2012;157(12):865-877.
- Kvarstein G, Måwe L, Indahl A, et al. A randomized double-blind controlled trial of intra-annular radiofrequency thermal disc therapy - a 12-month follow-up. Pain. 2009;145(3):279-286.
- Keskimäki I, Seitsalo S, Osterman H, Rissanen P. Reoperations after lumbar disc surgery: a population-based study of regional and interspecialty variations. Spine (Phila Pa 1976). 2000;25(12):1500-1508.
These references describe surgery, injections and conservative care for lumbar disc herniation and sciatica in general. None of them tests a care program at Chiropractic Specialty Center.
The Author of Non-Surgical Slipped Disc Treatment: Surgery Risk, 8 Checks
Non-Surgical Slipped Disc Treatment: Surgery Risk, 8 Checks was written by Yama Zafer, D.C., who has 30+ years in chiropractic and physiotherapy and founded Chiropractic Specialty Center in Kuala Lumpur in 2006.
Last Updated: Non-Surgical Slipped Disc Treatment in KL: Surgery or Not?
Non-Surgical Slipped Disc Treatment in KL: Surgery or Not? was last reviewed and updated on October 19, 2026.