
Neck Pain Treatment in Kuala Lumpur: Symptoms, Causes and Care
What Are the Symptoms of Neck Pain?
Neck pain can ache, burn, feel sharp or feel like a heavy, tight band. It may come and go with certain movements or positions, or build through a day at a desk. The common symptoms are:
- Stiffness, with difficulty turning or tilting the head.
- Pain that is worse after holding one position for a long time and easier with gentle movement.
- Tight, tender or spasming muscles across the back of the neck and the tops of the shoulders.
- Pain between the shoulder blades or around the shoulder.
- A headache that starts at the base of the skull.
- Pain, tingling, burning, numbness or weakness that travels into an arm or hand.
- Dizziness, jaw discomfort or ear symptoms alongside a sore neck.
Where neck pain is felt is one clue, and the structure responsible is worked out from the history and examination together. In my experience, a joint, nerve or disc problem in the neck can at times feel muscular. A pulling feeling alone does not show the cause.
“Cervicalgia” is simply the clinical word for neck pain and names no cause. “Cervical radiculopathy” means a nerve root in the neck is involved, usually with arm pain, numbness or weakness. “Myelopathy” means the spinal cord itself is affected, which calls for prompt assessment.
For the detailed process used before a service is selected, read what happens during a neck pain assessment in Kuala Lumpur.
What Do Neck Movements Show? Three Simple Clues
In my video further down this page, I show three movement clues that the examination then checks:
- Turning to one side: discomfort on the same side you turn toward could be a joint involvement. A joint problem can come with a muscle problem or follow one.
- Tilting the head up and down: discomfort in the upper back or a shoulder blade usually means a joint or a disc involvement.
- Turning both ways: the range should be equal in both directions, and a restriction on one side could be a muscle or a joint involvement.
These clues guide the examination and never replace it.
Booking a Neck Pain Assessment in Kuala Lumpur
For neck pain or a stiff neck without the warning signs described on this page, a first visit starts with your history. An examination of movement, strength, sensation and reflexes follows, and the findings are explained before any care is discussed. Please call or WhatsApp before visiting.
Directions and opening hours for each center are on the CSC contact and directions page. More detail is on the Bukit Damansara contact page and the Bandar Sri Damansara contact page, or call or message a center directly:
- Bukit Damansara (KL, main center): Call +603 2093 1000 or WhatsApp +60 17 269 1873 to see the Bukit Damansara / KL center.
- Bandar Sri Damansara (KL): Call +603 6262 5777 or WhatsApp +60 12 455 6939 to see the Bandar Sri Damansara center.
How the Cervical Spine Works and Why It Matters
The neck has seven vertebrae, six discs, small paired joints at the back and eight nerve roots on each side that serve the shoulders, arms and hands. It carries the head, and in my words, the neck moves all day: we nod, turn and look, and it cannot be kept still.
In my view, the whole neck works as one chain. Apart from the top two joints, C4-C5 and C5-C6 are its workhorses. A neck disc, as I note in my Back Pain to Leg Pain talk, has about 15 rings of fibers, against about 25 in a low-back disc.
A level named on a scan report is one finding to weigh against the examination. A muscle that feels tight may be reacting to pain rather than causing it, which is why the history, the examination and any imaging are read together.
What Do the Upper and Lower Cervical Levels Control?
The upper cervical region includes the occiput, C1, C2, and often C3. It contributes substantially to head positioning and rotation. The lower cervical region, including C4-C5, C5-C6, C6-C7, and C7-T1, helps transfer load between the neck and upper back. It also contains nerve-root pathways that serve movement and sensation in the arms.
The individual level guides explain anatomy, imaging terms and region-specific questions. A symptom can point toward a region, and the level involved is judged from the examination and, where needed, imaging. Use these guides to understand report language and prepare questions.
| Guide | What it covers | Read more |
|---|---|---|
Upper cervical overview | C0-C3 region, head-neck movement, assessment limits | |
Occiput-C1 | Skull-atlas relationship and upper-neck questions | |
C1-C2 | Atlas-axis rotation and upper-neck questions | |
C2-C3 | Upper-to-mid cervical transition | |
C3-C4 | Mid-cervical joint, disc, and nerve terminology | |
C4-C5 | Mid-to-lower cervical transition | |
C5-C6 | Commonly reported lower-cervical disc and nerve terminology | |
C6-C7 | Lower-cervical disc, joint, and nerve questions | |
C7-T1 | Cervicothoracic junction and C8-related questions |
How Are Cervical Disc Bulge, Protrusion, Prolapse and Herniation Different?
I describe disc damage in stages, in this order, and “slipped disc” is the everyday name for all of them:
- Bulge: the disc’s fibers have swollen more than usual. A true bulge does not press on the spinal cord or the nerves.
- Protrusion: the center of the disc moves outward toward the spinal canal or a nerve opening without breaking through the outer fibers.
- Prolapse: barely contained. A few remaining outer fibers keep the center from rupturing into the spinal canal.
- Herniation, the same as a rupture: the center breaks through the outer fibers and can come in contact with the spinal cord or a nerve.
- Extrusion: the center is pushed out to the edge of the disc. It needs prompt assessment, which does not automatically mean surgery.
- Fragmentation: the last and most dangerous stage, when a piece of the center breaks off and floats free in the spinal canal.
Scan reports often name these changes differently. Many follow the naming in a 2014 guide by three North American spine and radiology societies, written for the lower back (Fardon 2014) [8]. In it, protrusion and extrusion describe the shape of displaced disc material rather than stages, and prolapse and rupture are nonstandard terms. The guide also notes that some practitioners call a protrusion contained, still held in by the outer fibers, and an extrusion uncontained. My stages above follow how I see a contained neck disc problem become one that has broken out. A report and I may therefore name the same disc differently.
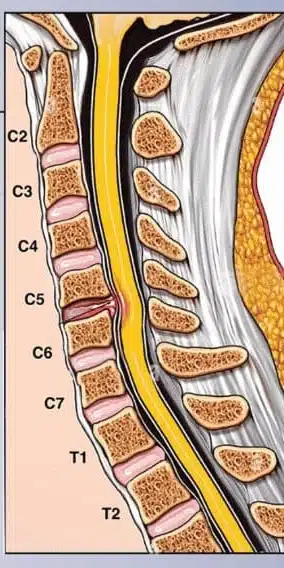
The word bulge is often used loosely, even in some scan reports, for a disc that has gone further. By my definition, a disc that presses on the spinal cord or a nerve is a prolapse or a herniation, not a bulge. On my scale of 0 to 10 for how serious a disc problem is, a true bulge scores 1 or 2; once the disc presses on the sac that holds the spinal cord, or on a nerve, the score is 3 to 5. Pain, severity and the right care are judged from the symptoms and the examination, not from the word on the report.
The spinal level, direction, size, nerve-root or spinal-cord relationship, neurological findings, function, and progression are interpreted together. Disc damage is often silent: in my experience, the most common symptom of a damaged disc is none. That is why a scan is read with the examination before any procedure or outcome is discussed.
Read the dedicated guides for cervical disc bulge, disc protrusion, disc prolapse, and disc herniation.
What Do Cervical Spondylosis, Osteophytes, and Stenosis Mean?
Cervical spondylosis is a broad term for wear-related changes in the neck joints and discs. Imaging may describe reduced disc height, osteophytes (bone spurs), facet changes, uncovertebral changes, or narrowing around the spinal canal or nerve openings. These findings can be relevant, incidental, or one part of a larger presentation.
In my experience, most adults with a stiff neck have some of these changes, and seeking help for that stiffness is normal. I have yet to see anyone in their fifties without some spondylosis or some disc bulge. The uncovertebral joints are small joints that act like guardrails at the sides of the neck bones. Spurs near them are readily seen on an X-ray and are often what a report calls spondylosis. They also sit close to the vertebral artery, which is one reason forceful neck pulls are avoided.
Spinal stenosis means less room in the spinal canal or the nerve openings. How much it matters depends on whether the spinal cord or a nerve root is pressed, and on what the hands, balance and walking show at the examination.
Use the cervical spondylosis guide and spinal stenosis guide for deeper imaging terminology and referral boundaries.
What Causes Neck Pain?
Neck pain often has several contributors at once. Long periods at a screen, a recent rise in lifting, poor sleep, an old collision, jaw clenching and stress can all play a part. One factor may matter more than another, and the balance can change over time.
According to the statistics I have read, 40% of people with chronic neck or back pain have disc bulges and herniations. Another 45% have joint problems, and the remaining 15% have muscular or other forms of disc problems. In my experience, neck problems often start in the muscles. If that goes on long enough, the joints are affected, and as it progresses, the discs, with a disc bulge, a protrusion or a herniation.
As I see it, most wear-related changes in the neck, such as disc wear and cervical spondylosis, follow an injury, sudden or repeated, or repeated harmful strain. Finding the root cause of one person’s sore neck takes a thorough assessment by a qualified provider. My Back Pain to Leg Pain talk warns that neck pain is quickly overtaking back pain, and that our posture and our technology are the main reasons. Craning the head forward over a laptop or a phone, in my view, strains the base of the neck as much as its top, or more. The other common starting points are:
- A strained or spasming muscle after an awkward movement, a long drive, a heavy lift or a night in an awkward sleeping position.
- A sudden jolt, such as whiplash, a fall or a sports injury.
- A rise in lifting, carrying, training or overhead work.
- Jaw clenching, poor sleep and stress.
Posture matters, whether sitting, standing, sleeping or driving. In my words, “If you take care of your posture, your spine will take care of you.” At a desk, the knees are level with the hips or slightly above, and the feet sit directly under the knees. The backs of the knees clear the chair, and the eyes look straight ahead, slightly below the top of the screen. A laptop is raised or attached to a monitor, and two screens are used equally with the gap in front. The phone sits on the left for a right-handed person, or a headset is used.

With neck pain, I advise standing up every 15 to 20 minutes and walking or moving for 30 seconds to a minute. Without a neck or back problem, once every 30 to 40 minutes will do. Strength, sleep and workload all count as well.
For neck pain linked to phones and other screens, use the text-neck guide.
For broader multi-region workplace concerns, use the Office Syndrome guide.
Common Neck Pain Patterns and Why They Matter
The pattern of neck pain, what comes with it and how it started decide what comes first: routine neck care, a doctor’s review, imaging or urgent care.
| Neck pain pattern | Why the details matter |
|---|---|
Local neck pain or stiffness | Pain or tightness that stays in the neck, reduced turning or tilting, muscle guarding, pain after a sustained position, or pain that changes with movement. |
Neck pain and upper-back pain | Pain between the shoulder blades, shoulder-blade fatigue, desk or driving strain, or symptoms spanning the lower neck and upper thoracic region. |
Neck pain with shoulder or arm symptoms | Pain that extends toward the shoulder or arm, with or without numbness, tingling, burning, altered sensation, grip change, or weakness. |
Neck pain with headache | Pain at the upper neck or base of the skull with a headache pattern. Migraine, visual, dental, neurological, vascular, medication-related, and other causes may overlap. |
Neck pain with dizziness or balance change | Dizziness has many possible causes, the neck among them. New, severe, persistent, trauma-related, or neurologically associated dizziness may need medical assessment. |
Neck pain after a collision or fall | Whiplash or trauma changes the assessment. Fracture, instability, neurological change, and unusual headache require appropriate medical consideration. |
Neck pain with jaw or ear symptoms | Clenching, chewing difficulty, jaw clicking or locking, dental factors, tinnitus, ear fullness, or facial symptoms may require dental, medical, audiological, or TMJ-specific assessment. |
Night or systemic neck pain | Fever, unexplained deterioration, significant night sweats, cancer history, immune-related concerns, or progressive symptoms may require medical investigation. |
How Are the Upper Back, Shoulder Blade and Rotator Cuff Involved in Neck Pain?
In my rhomboids video, I describe the upper back as the foundation for the neck. The trapezius and rhomboids tie the neck, the shoulder blades and the upper back together, and a laptop all day or a head bent over a phone strains them, often with trigger points between the shoulder blades.
Shoulder pain can come from the rotator cuff or the shoulder joint itself, from the neck, or from both. So neck and shoulder movement, strength and sensation are compared at the examination before the source is decided.
Read the neck and upper-back guide, the upper-back guide, the shoulder-blade guide, or the shoulder guide.
What Does Neck Pain With Arm or Hand Symptoms Mean?
Pain, numbness or tingling that travels into an arm or hand can come from a nerve root in the neck, a nerve trapped at the elbow or wrist, the shoulder or a medical condition, so the examination checks each. In my experience, if tilting the head back brings on the arm symptoms, more than likely a nerve is pinched, by a disc or by spondylotic change. When neck pain comes with pain, numbness or tingling down an arm, I never let anyone crack or twist the neck. That includes rotatory exercises, whoever gives them.
Trouble making a fist or opening a bottle or a jar points, in my experience, to the lower neck at C6-C7 or C7-T1.
Arm or hand weakness that keeps getting worse should not be ignored. It calls for a careful assessment by a competent provider, and conservative care can continue only while the weakness itself is improving. Hand clumsiness, a change in walking, or symptoms in several limbs are assessed promptly too, because these findings may involve the spinal cord. As my Back Pain to Leg Pain talk explains, a disc pressing on the cord in the neck can reach the legs, with weakness or trouble walking, and the higher in the neck it sits, the more of the body it can affect.
Use the pinched-nerve guide and nerve-pain guide for deeper nerve-specific information.
Can a Stiff Neck Cause Headaches or Dizziness?
Yes, it can. I have seen upper neck problems bring on headaches and migraines, mild to severe, and at times mental fog or dizziness. That is not the usual picture, but it does happen. Both symptoms have many other causes as well, such as eyesight, medication, the jaw, the inner ear or an illness. A sudden severe headache unlike any before, or a headache with new changes in vision, speech, the face, balance or a limb, needs urgent medical assessment.
Dizziness that is new, severe or lasting, or that comes with fainting, hearing loss or other new nerve symptoms, is checked by a doctor before a routine visit for neck pain.
Read the headache and migraine guide and the upper-cervical guide for more on each.
What Is Different After Whiplash or Another Neck Injury?
A collision, fall or sports injury changes the assessment of neck pain. Symptoms can start straight away or days later, so the history covers how it happened, any blow to the head or loss of consciousness, severe headache, dizziness and arm or leg symptoms. Those answers decide whether an X-ray, a doctor or a hospital comes before any neck care.
In my experience, C6-C7 is rarely damaged alone: it usually goes with trouble at C4-C5 or C5-C6, often after a road accident, whiplash or a sports injury. That is why the whole neck is examined after an injury, not only the part that hurts most.
The whiplash guide covers trauma-related neck pain in full.
How Do Jaw, TMJ, Tinnitus, and Ear Symptoms Overlap With the Neck?
In my experience, a long-standing problem at the top of the neck can bring on jaw trouble, and trouble in the jaw can load the upper neck in return, so the jaw joints are checked along with the upper neck. Clenching, clicking, locking or pain when chewing may also need a dentist.
Tinnitus and ear fullness have many possible causes. New tinnitus in one ear, sudden hearing change, pulsatile tinnitus, severe dizziness, neurological change, or other concerning features call for a medical or hearing assessment. The cause may lie outside the neck and jaw.
For jaw problems, see the temporomandibular joint guide. For ringing in the ears, see the tinnitus guide.
When Should Medical Assessment Come Before Neck Pain Treatment?
Medical or urgent assessment comes first whenever a routine visit for neck pain could delay necessary care. Red flags are safety prompts, and the diagnostic accuracy of most of them is unproven. Clinical guidelines also show little agreement on which ones to use, so they are weighed with the history, examination, and clinical judgment (Feller 2024; Finucane 2020) [3,4].
| Situation | Examples |
|---|---|
Possible stroke, vascular, cardiac, or breathing emergency | New facial droop or speech difficulty, sudden one-sided weakness, collapse or fainting, chest pain, severe shortness of breath, or sudden severe dizziness with neurological change. |
Possible spinal-cord or severe nerve involvement | Arm or hand weakness that keeps getting worse, marked hand clumsiness or loss of coordination should be assessed promptly and carefully by a competent provider. So should a new change in walking or balance, or symptoms in several limbs. A new loss or change of bladder or bowel control needs urgent medical attention at a hospital emergency department straight away, within hours. Several causes are possible, and some may call for an invasive procedure, but an assessment does not automatically mean surgery. |
Serious injury | High-impact collision, fall with severe neck pain, suspected fracture, marked deformity, or inability to use an arm after trauma. |
Systemic illness or infection concern | Fever with severe neck or spinal pain, unexplained deterioration, significant night sweats, cancer history with new progressive symptoms, or immune-related concerns. |
Severe or unusual headache | A sudden “worst” or unfamiliar headache, headache after significant trauma, or headache with new visual, speech, facial, balance, coordination, or limb changes. |
Pregnancy or postpartum warning signs | Bleeding, fluid leakage, reduced fetal movement, fainting, fever, severe abdominal or pelvic symptoms, wound concerns, or another urgent maternity change. |
How Is Neck Pain Assessed?
I do not rush the assessment of a neck: it takes anywhere from 30 minutes to two hours. It starts with the history: when the pain began, whether it followed an injury, what makes it better or worse, whether it travels, and how work, sleep and driving are affected. The examination then covers how the neck and upper back move, using the three movement clues above, with strength, sensation and reflexes in both arms.
For the lower neck, I compare grip, the OK sign and pinprick feeling in the little and middle fingers, always on both sides. A test that would stir up the symptoms is changed or left out. Any MRI, X-ray or specialist letter is weighed with these findings, never as a diagnosis on its own.
The neck pain assessment page explains the detailed assessment process and how to prepare. It covers medication, bone health, neurological checks, imaging review, consent, fees, privacy, and referral decisions.
Do You Need an MRI or X-Ray for Neck Pain?
Not every patient with neck pain needs imaging. In my practice, an X-ray is ordered only after a thorough assessment and only when it is indicated. For a neck complaint, it is a sectional X-ray of the neck, and a full-spine X-ray is for scoliosis. When a disc problem is suspected, I ask for imaging rather than guess a final diagnosis. When a nerve root in the neck may be involved, a cervical MRI is my first-choice test. Imaging may also be needed to investigate warning signs, review prior surgery or answer a referral question.
An MRI is the gold standard: it uses no radiation and shows bone, joints, muscles, ligaments and the space the nerves occupy. An X-ray is cheaper, but it shows only bone. Bring existing MRI, X-ray, CT, nerve-study or specialist records that relate to the current problem. Bring the scans themselves, on CD or film, as well as their reports.
Imaging findings are correlated with symptoms, examination, and function. On cervical MRI, Smith and colleagues’ 2021 review found spinal cord compression from degenerative change in about 24% of healthy people without symptoms [1]. So an “abnormal” report is weighed against the symptoms before any one structure is held responsible. Equally, a report described as mild can sit alongside real difficulty with daily function. Imaging is one part of clinical reasoning, alongside the history and examination.
How Is Neck Pain Treated?
Neck pain is usually treated with conservative care: gentle chiropractic care, physiotherapy, hands-on soft tissue work and exercise. I have always recommended chiropractic and physiotherapy combined, because care cannot be comprehensive with a single approach. The plan is chosen from the history, the examination, the person’s goals and the response over time. Medical care, imaging, medication or a specialist opinion comes first when warning signs or worsening nerve findings call for it.
Otherwise, surgery and injections remain a distant last resort. Surgery has its place, and there are times I cannot help, but with a disc problem, even a herniation, focused conservative care, properly given, comes first. An adjustment addresses a vertebra’s position, but the muscles, ligaments and disc also need rehabilitation, re-education and strengthening. So ultrasound or high-intensity laser, used with gentle myofascial and trigger point release, is often part of my plan.

| Care option | What it involves |
|---|---|
Chiropractic care | Gentle, non-rotatory adjustment of the neck and upper back, by hand or with the Activator® instrument, plus soft tissue work. The choice follows the joint, muscle and nerve findings. |
Physiotherapy by registered physiotherapists | Hands-on soft tissue and joint work, exercise, task practice and education, built on an assessment of mobility, strength, endurance and movement control. |
Guided rehabilitation and exercise | Neck and upper-back mobility, shoulder-blade control, strength and endurance work, increased step by step toward work, sport and daily tasks, and reviewed as it progresses. |
Education and self-management | Movement variety, screen and workstation changes, sleep position, pacing, and a simple record of symptoms and function. |
Supportive modalities | Cold, laser, ultrasound or electrotherapy where available and suitable, used alongside active care, exercise and review. Heat is seldom used, and never on a neck with a facet joint or disc problem or on an inflamed area. |
Medical, imaging, injection, or specialist care | The right first step when trauma, warning signs or worsening nerve findings point to another professional or an investigation. A major loss of function or a lack of progress can also call for it. |
For nonspecific neck pain, Wilhelm and colleagues’ 2023 review of 22 studies found that manual therapy combined with exercise eased pain and disability more than exercise alone. It eased them about as much as manual therapy alone, and the certainty of this evidence was low to moderate [2]. A 2023 review by Colman and colleagues found that exercises for the muscles at the back of the neck may also reduce pain and disability, though few trials have tested them on their own [5].
For physiotherapy for neck pain, the page on physiotherapy services in Kuala Lumpur explains how exercise and hands-on methods are combined and how progress is judged.
Exercise that rebuilds stability and then strength after neck pain is set out phase by phase under spine and joint rehabilitation.
Every other service is listed in the complete CSC services hub.
What Is the Best Treatment for Neck Pain?
No single neck pain treatment is best for every sore or stiff neck. The right choice depends on what the examination finds, whether a nerve is involved and how long the neck has hurt.
In my view, any care depends on an accurate diagnosis and a proper plan. It also depends on care carried out with as few flaws as possible, and on changes to posture, habits and daily activity. A neck pain plan can be checked against these points:
- Warning signs first: stroke-like symptoms, a serious injury or fever with severe neck pain need medical care before any routine visit (see the warning signs).
- A registered practitioner: in Malaysia, chiropractors must register with the Traditional and Complementary Medicine Council. Registration can be checked online through the Ministry of Health’s Traditional and Complementary Medicine Division.
- An examination before any care: how the neck moves, strength, sensation and reflexes, with any MRI or X-ray weighed against the findings (see the assessment).
- Research: for neck pain with no specific cause, a 2023 review found manual therapy plus exercise eased pain and disability more than exercise alone. The certainty of that evidence was low [2].
- Methods suited to the neck: gentle, non-rotatory care kept within what the person can comfortably tolerate (see how methods are selected).
- Home steps that suit the neck: short, comfortable movements, screen and pillow changes, and no forceful self-cracking (see first steps at home).
- Measured progress: with no improvement by the fifth session, the chiropractor reassesses. With none by the tenth, whether to stop or continue is discussed and decided together. A lack of progress can also lead to a referral.
- Surgery or injections last: considered after focused conservative care, properly given, has not worked, or sooner if warning signs or worsening nerve findings appear (see care options).
Before choosing, call or WhatsApp the centers being considered, describe the neck pain and ask how each would examine it.
How Are Chiropractic Methods Selected for Neck Pain?
Suitability comes from the assessment rather than from a technique’s name. The choice weighs the body region, history, age, comfort, bone and joint health, and nerve findings. Medication, pregnancy, past injury or surgery, blood vessel considerations and the response so far count too. Every manual method carries some risk, and each suits some presentations better than others.
With the patient’s consent, neck care at CSC uses gentle, non-rotatory methods. These are specific mobilization by hand, the Activator® instrument, table-assisted methods and soft tissue work, or care without a manual procedure when that suits better. Care is kept within what you can comfortably tolerate. Discomfort during care means it is being done too aggressively, so tell the clinician at once.
My motto has always been “No pain, more gain.” A cracking or popping sound, when it happens, is a cavitation, a release of gases from the joint. It is not a sign that a joint was corrected.
Cracking and twisting should not be done on a spine with a damaged disc, even by a very experienced chiropractor. I am not a big fan of rotary manipulation: I use it only when I am 100% sure there is no spinal disc damage, and in practice that is almost never. For people in their 40s or older with degenerative changes, bone spurs or a pinched nerve, I do not recommend cracking methods.
Read the chiropractic adjustment guide, the Activator® guide, and the chiropractic technique comparison for method-specific information and limitations.
Are Spinal Decompression, Traction, or Other Modalities Used?
Cervical traction or spinal decompression may be considered for selected neck pain or cervical-radiculopathy presentations after screening. The intended purpose, neurological findings, available equipment, contraindications, comfort, and response are reviewed first. Danish national guidelines (Kjaer 2017) suggest traction for recent-onset cervical radiculopathy. They note that their recommendations rest on low-quality evidence or on consensus, so its use depends on the diagnosis [6].
Where it is used, decompression is a controlled form of traction, and symptoms and function are checked at each review.
Read the spinal decompression guide for service-specific indications, exclusions, and evidence limits.
Y-Strap and Ring Dinger Neck Pulls: What CSC Uses Instead
In place of Y-Strap or Ring Dinger-style high-force traction, Chiropractic Specialty Center uses the gentle, low-force and instrument-assisted methods described above. They are chosen after assessment, with disc, nerve, and vascular safety in mind.
In my view, these pulls are dangerous because the neck has small joints and soft discs. The vertebral artery, which is even more critical than the nerves, runs through small openings beside the neck bones. Grabbing the sides of the neck and yanking is absolutely a no-no, and years of doing it without a problem do not make it safe. Extra care is needed with birth control pills, high blood pressure, a disc bulge or herniation, spondylosis or an unstable neck. If someone wants to do this to you, ask them to stop. A sudden pull can turn a mild disc bulge into a severe herniation, or tear the fibers of a degenerated disc.
Neck care must be safe, focused and specific, and it never needs to be aggressive or violent. The video below explains how the neck responds to sudden, forceful traction, and the forceful neck-pull safety guide covers the topic in more depth.
Baca halaman ini dalam Bahasa Malaysia: Rawatan Sakit Leher di Kuala Lumpur: Gejala, Punca dan Pilihan Rawatan